API Peptide: tesamorelin FDA approval
The approved indication has a particular population and a particular fat compartment. Both are essential to the result.
Is tesa peptide FDA approved?
Yes. Tesamorelin received FDA approval in 2010 to reduce excess abdominal fat in adults with HIV-associated lipodystrophy, the abnormal fat distribution associated with HIV treatment. The NIH LiverTox account of tesamorelin describes that approval. “Tesa” is a shortened name used for tesamorelin; it adds no separate approval.
The approved indication concerns excess visceral fat, the fat deep around abdominal organs. General weight loss, anti-aging and cognitive enhancement remain outside that indication. A clinician’s off-label prescription leaves the FDA-approved indication unchanged. For tesamorelin, I put HIV-associated lipodystrophy first: a broad phrase such as belly-fat reduction loses the part that made this a specific medical use.
An abdominal scan, in square centimetres
A six-month randomized trial in 50 adults receiving antiretroviral treatment for HIV reported a treatment effect of −42 cm² in visceral fat area against placebo. That is an area measured through a slice of the abdomen. It gives no conversion into pounds of body weight. Liver fat also fell more with tesamorelin.
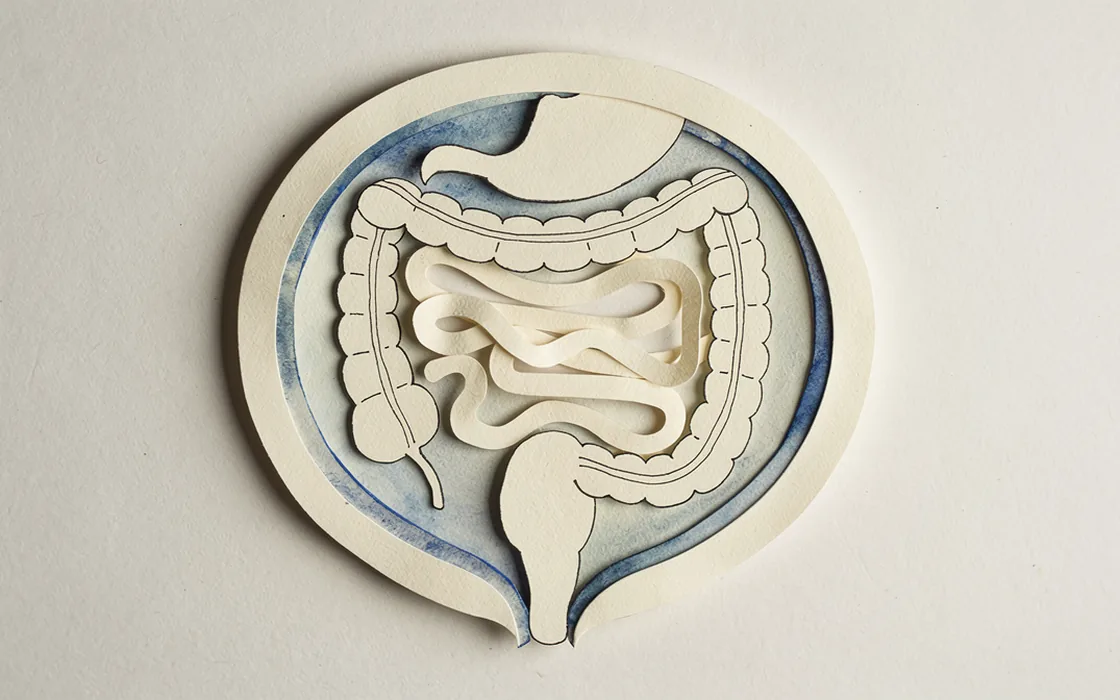
For me, the unit makes the result more interesting: the experiment asks about a particular depot of fat rather than treating all lost weight as interchangeable. The illustration below locates that depot; its shapes carry no measurement from a participant.
The hormone response
Tesamorelin is a modified 44-amino-acid analogue of growth hormone-releasing hormone. It prompts the pituitary gland to release the body’s own growth hormone in pulses; growth hormone then stimulates liver production of IGF-1, a signal involved in tissue growth. An altered end of the peptide resists rapid breakdown.
In a two-week experiment involving 13 healthy men, overnight growth hormone and IGF-1 rose, while fasting glucose and insulin-stimulated glucose uptake did not change significantly. That short experiment answers a hormone-response question in healthy men. The abdominal-fat trials answer a different question in adults living with HIV. I would resist joining the two into a general rejuvenation claim.
Tesamorelin at 52 weeks
The 52-week programme in adults with HIV-associated abdominal fat accumulation included 273 tesamorelin recipients and 137 placebo recipients. Visceral fat remained 18% below baseline during treatment; glucose changes were not clinically significant. Fat reaccumulated after treatment stopped.
A 2026 meta-analysis of five randomized trials found reductions in visceral fat, trunk fat and hepatic fat, with increased lean body mass, and reported no serious adverse events. The studies concerned HIV-associated lipodystrophy. The trial findings leave longer-term risks open, particularly questions involving sustained IGF-1 elevation. Active malignancy is a labelled contraindication.
LiverTox judged tesamorelin an unlikely cause of clinically apparent liver injury, noting no attributable reported cases or new serum-enzyme elevations in trials. That is reassuring about this particular safety question. It does not settle every consequence of prolonged hormone stimulation. Tesamorelin is prohibited in sport at all times under the World Anti-Doping Agency’s hormone and growth-factor category.
The unresolved tesamorelin question concerns longer-term benefit and risk in HIV-associated lipodystrophy. The study settings table helps explain why an obesity trial cannot answer it by substitution.